Lecture 4 — Abortion
Part B: Abortion and the Law, in the US and Around the World
An Introduction to Bioethics.
On Call in Lubbock
You are the doctor on call in Lubbock, Texas. A 26-year-old patient arrives at 20 weeks after her water has broken. She has a fever of 101.8°F, and test results are still pending. The fetus cannot survive at this stage. Continuing the pregnancy is likely to lead to serious infection, including sepsis. Right now her vital signs are stable, and there is still fetal cardiac activity.
Texas law allows abortion only for “a life-threatening physical condition” that creates “a serious risk of substantial impairment of a major bodily function.”
- What would you want to do for her, clinically, and why?
- Does the wording of the law clearly allow it?
- If the team waits until she is much sicker, has the law already harmed her, even if she survives?
After You’ve Discussed
Note
The exception is clear on paper and unclear at the bedside. Previable rupture of membranes, sepsis from an incomplete miscarriage, an ectopic pregnancy at risk of rupture: at what point is the threat serious enough? The statute is read by prosecutors, not physicians. Act too early and a clinician risks a felony carrying up to 99 years; wait too long and the patient’s life is at risk.
In Zurawski v. Texas, more than twenty women denied care under this statute sued. In May 2024 the Texas Supreme Court ruled against them, holding that the “medical emergency” language was already clear and that physicians were misreading it. The paired case study follows Kate Cox, who was refused the same exception in December 2023.
Today
By the end of Part B, you will be able to:
- Trace how abortion law has varied historically, from common-law “quickening” through 19th-century criminalization
- Explain precedent and stare decisis in plain English
- Reconstruct the Roe and Dobbs majorities in standard form and identify the load-bearing premise of each
- Describe the post-Dobbs landscape: state tiers, medication abortion, and conflicts between states
- Place the US within four global regulatory models
A Brief History
Before the 19th Century
- In ancient Greece and Rome, abortion and infant exposure were widely practiced, lightly regulated, and not understood through anything like fetal personhood. Roman law treated the fetus as part of the mother.
- Aristotle held that the soul entered the fetus at 40 days (male) or 90 days (female), a view that shaped European thought for two millennia.
- For roughly seven hundred years, English common law, inherited by colonial America, made abortion a crime only after quickening, the first felt fetal movement at about 16–20 weeks. Even then it was a misdemeanor, not murder.
- The line was evidential, not metaphysical: quickening was the first reliable sign the pregnancy was real. Roe later leaned on this history.
The 19th-Century Criminalization Campaign
Between roughly 1830 and 1880, every US state outlawed abortion at every stage of pregnancy. The driving force was not religion but a professional movement led by the American Medical Association (founded 1847).
- Dr. Horatio Storer launched an AMA campaign in 1857 arguing that scientific embryology had shown fetal life began at conception — quickening, he said, was obsolete.
- The campaign also served the AMA’s interest in displacing midwives and homeopaths from reproductive care.
- By 1880, abortion was a felony in every US state. The Catholic Church did not formally adopt its current position until 1869 (Pope Pius IX).
The Back-Alley Era (1900–1973)
Criminalization did not end abortion; it moved it underground.
- 1930s: illegal abortion was a leading cause of maternal death — 5,000 to 17,000 deaths per year.
- Sherri Finkbine (1962): a Phoenix TV host took thalidomide, learned of its effects on fetal development, and traveled to Sweden for an abortion. A turning point in US opinion.
- The Jane Collective (Chicago, 1969–1973): a clandestine, mostly non-medical network that performed an estimated 11,000 abortions before Roe.
- By the early 1970s, fourteen states had reformed their laws; four (Alaska, Hawaii, New York, Washington) had legalized abortion on request before Roe.
The Constitutional Arc: Roe → Casey → Dobbs
How to Read a Ruling
- A precedent is a prior decision that later courts treat as binding. It is what makes law predictable.
- Stare decisis (“stand by things decided”) says to follow precedent even when you disagree. It is a presumption, not an absolute.
- Courts overturn precedent for four standard reasons: the rule is unworkable; society has not relied on it; it fits badly with related law; or its factual assumptions have failed.
- The majority opinion binds. A concurrence agrees but adds reasoning; a dissent has no force now, though dissents sometimes become later majorities.
- A ruling is an argument whose premises are claims about text, history, and precedent, so the tool from Part A still works.
Roe v. Wade (1973) — What It Actually Held
- A 7–2 decision written by Justice Harry Blackmun.
- Held that the Fourteenth Amendment’s Due Process Clause implicitly protects a “right of privacy” broad enough to cover the abortion decision.
- Created the trimester framework: 1st — woman and physician decide; 2nd — state may regulate for maternal health; 3rd — state may prohibit except for life or health.
- Drew on the common-law history of quickening.
Framed not as creating a new right but as recognizing one already implicit in Griswold (1965, contraception) and Loving (1967, interracial marriage).
Roe in Standard Form
The Roe Majority Argument
Blackmun, J., for a 7–2 Court (Supreme Court of the United States 1973)
- The Fourteenth Amendment’s Due Process Clause protects a sphere of personal liberty (the “right of privacy”) that the government may not enter without a compelling reason.
- The decision whether to terminate a pregnancy lies inside that sphere — it is among the most intimate and consequential choices a person can make.
- The state has two interests that might override that liberty: protecting maternal health, and protecting “potential life.” Neither becomes compelling until certain points in pregnancy (roughly the second and third trimesters, respectively).
- Therefore, before those points, the state may not prohibit abortion.
Planned Parenthood v. Casey (1992)
- 5–4 decision; unusual joint opinion by three Republican-appointed justices (O’Connor, Kennedy, Souter).
- The Court was expected to overturn Roe. Instead it reaffirmed the central holding on stare decisis grounds.
- Replaced the trimester framework with viability as the dividing line and the undue burden standard — states may regulate, but not place substantial obstacles before viability.
Casey works the four standard reasons for overturning precedent (workability, reliance, coherence, factual change) through in plain view — a controversial exhibit of stare decisis in action.
Dobbs v. Jackson Women’s Health (2022)
- 6–3 decision (5 for full overruling, 1 for the narrow result only), Justice Alito writing.
- The case challenged Mississippi’s 15-week ban — well before viability under Casey.
- The Court overturned both Roe and Casey entirely and returned the question to state legislatures. Within a year, 13 states activated “trigger laws.”
- Justice Thomas’s concurrence suggested the same reasoning could reach Griswold, Lawrence, and Obergefell.
Dobbs in Standard Form
The Dobbs Majority Argument
Alito, J., for a 5-justice majority (Supreme Court of the United States 2022)
- Rights protected by the Due Process Clause beyond those listed in the Bill of Rights must be “deeply rooted in this Nation’s history and tradition” and “implicit in the concept of ordered liberty.”
- Abortion was a crime in most American states from the mid-19th century until Roe in 1973 — so it is not deeply rooted in our history and tradition.
- Stare decisis is a presumption, but it gives way when a prior decision was “egregiously wrong” from the start, has proved unworkable, and has not generated strong reliance interests of the kind that justify keeping it.
- Roe and Casey meet that test.
- Therefore, Roe and Casey are overruled; the Constitution does not protect a right to abortion; the question returns to the states.
Activity — Circle the Weakest Premise
You now have both Roe and Dobbs in standard form. The dispute between them is not really about whether abortion is moral — it is about what the Constitution requires.
Write or discuss:
- In the Roe argument, which premise (P1, P2, P3) carries the most weight, and which would a critic most likely target?
- In the Dobbs argument, the same question. (Hint: look hard at P1 — is “deeply rooted in history and tradition” really the right test?)
- Both arguments could be valid while disagreeing fundamentally. If the fight is over which premises are true, how should you evaluate the next Supreme Court decision you read?
The Post-Dobbs US Landscape
Where Things Stand — A US Map
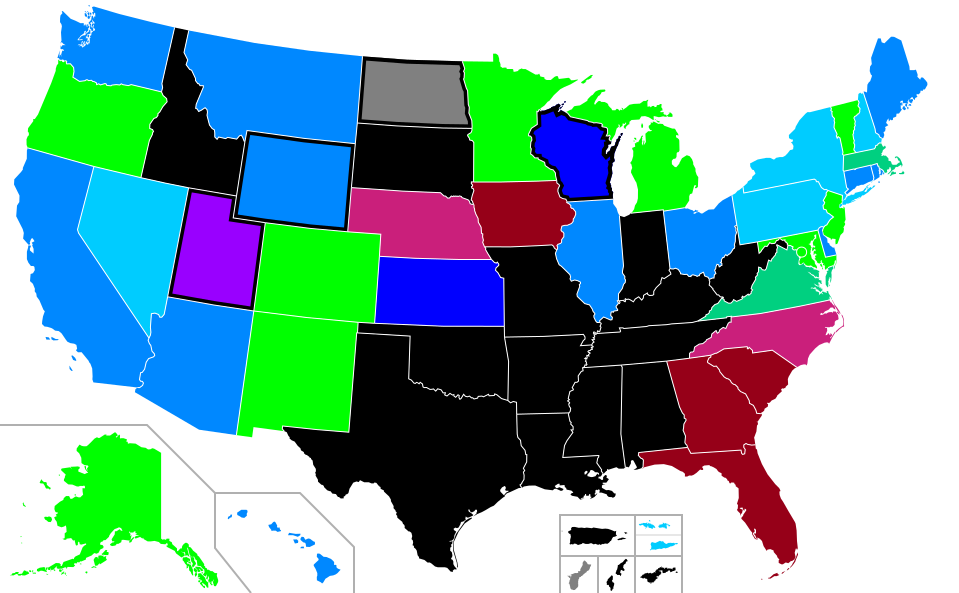
Wikimedia Commons, “Gestational limits for elective abortion in the United States” (May 2025). This map is a snapshot and is already out of date in places, Missouri in particular. Treat it as a picture of how varied the landscape is, not as a current legal reference. For live status, use the Guttmacher Institute or Center for Reproductive Rights trackers.
Five Regulatory Tiers
| Tier | Approx. gestational limit | Representative states |
|---|---|---|
| No state restriction beyond federal law | Up to viability or later (some allow later for health) | Colorado, New Jersey, Minnesota, Oregon |
| Viability standard (~24 wk) | Roughly the pre-Dobbs federal floor | California, Illinois, New York, Wisconsin |
| Mid gestational limit | 12–22 weeks | North Carolina (12 wk), Nebraska (12 wk), Utah (18 wk) |
| Six-week (“heartbeat”) laws | ~6 weeks LMP — before many know they’re pregnant | Florida, Georgia, Iowa, South Carolina |
| Near-total ban | Conception, with narrow life/health exceptions | Alabama, Arkansas, Kentucky, Mississippi, Texas, ~7 others |
Compiled from Guttmacher Institute state-policy tracking (Guttmacher Institute 2024). Tiers move constantly — verify before relying on any row.
Missouri: why a tier table is never finished. Missouri held a near-total ban until November 2024, when voters passed a constitutional amendment (Amendment 3) making reproductive freedom a state right — the first time a public vote overturned a near-total ban. What followed was two years of trench warfare: injunctions blocking the ban, the Missouri Supreme Court reinstating it on procedural grounds in May 2025, then further rulings restoring access, including a June 2026 circuit-court decision striking down most remaining restrictions.
The fight is not over. A new Amendment 3 — drafted by the legislature to re-ban abortion, with exceptions for life and, up to 12 weeks, rape and incest — goes before Missouri voters on November 3, 2026, in the middle of our term (Ballotpedia 2026). Watch it as it happens: you are seeing a state’s abortion law contested through courts and ballots at the same time.
Medication Abortion and the Comstock Act
- Since 2020, more than half of US abortions have been medication abortions (mifepristone + misoprostol).
- Pills travel by mail, across state lines, and from overseas, which makes abortion harder to ban completely.
- The Comstock Act of 1873, an obscenity statute still on the books, prohibits mailing items “intended for producing abortion.” For a century it was treated as a dead letter.
- Access to mifepristone by telehealth and mail now rests on a Supreme Court stay, a temporary order, not a settled rule.
Where the pill fight actually stands (as of July 2026). The federal government has not brought Comstock prosecutions, but the statute is now doing work in litigation rather than enforcement.
- States are suing the FDA. In Louisiana v. FDA, states argue that the FDA’s 2016–2023 decisions permitting telehealth prescribing and mail/pharmacy dispensing violated the Administrative Procedure Act and the Comstock Act.
- May 1, 2026: a Fifth Circuit panel sided with Louisiana and moved to roll back telehealth and pharmacy dispensing while the appeal proceeded.
- May 14, 2026: the Supreme Court stayed that order (Guttmacher Institute 2026). Mifepristone remains available by telehealth and mail for now. The Court did not rule on the merits — it froze the status quo while the case continues (KFF 2026). In a dissent, Justice Thomas argued the Comstock Act should be enforced as written.
- Separately, the FDA opened a safety review of mifepristone in late 2025. Several other mifepristone cases are paused awaiting its outcome.
Access to the most common method of abortion in the US currently rests on a stay, a temporary order, not a settled rule. What does it do to clinical practice when the legality of a standard treatment can change between one semester and the next?
Travel, Shield Laws, and Interstate Conflict
Travel for care. After Dobbs, abortion travel surged: an estimated 150,000–200,000 Americans now travel for abortion care each year.
Shield laws. A growing set of states (NY, MA, CA, CO, WA) have passed laws shielding their providers from out-of-state subpoenas and prosecutions when they ship pills to or treat patients from ban states. This is no longer a prediction — it is a live fight, likely headed to the Supreme Court under the Full Faith and Credit Clause.
Dr. Margaret Carpenter, a New York physician who mailed pills to patients in ban states, has been indicted in Louisiana, fined more than $100,000 in Texas, and protected by New York. All three claim to be applying the law correctly.
One doctor, two states, two legal universes. Dr. Margaret Carpenter, a New York physician, prescribed abortion medication by telehealth to patients in ban states.
- Louisiana indicted her on a felony charge — the first criminal case against a physician for mailing pills across state lines after Dobbs.
- Texas obtained a civil default judgment against her of more than $100,000.
- New York refused to cooperate. The governor declined Louisiana’s extradition demand, and in October 2025 a New York court rejected Texas’s attempt to enforce its judgment (Texas Tribune 2025).
Nothing has been resolved. Carpenter is charged in one state, fined in another, and protected in a third — and all three claim to be applying the law correctly. This is precisely the conflict the Full Faith and Credit Clause exists to settle, and it has not yet been settled.
Write or discuss: If the same act is a felony in Louisiana and lawful in New York, whose law should govern — the state where the doctor sits, or the state where the patient sits? What would each answer do to telemedicine generally, beyond abortion?
Abortion Law Around the World
A World Map
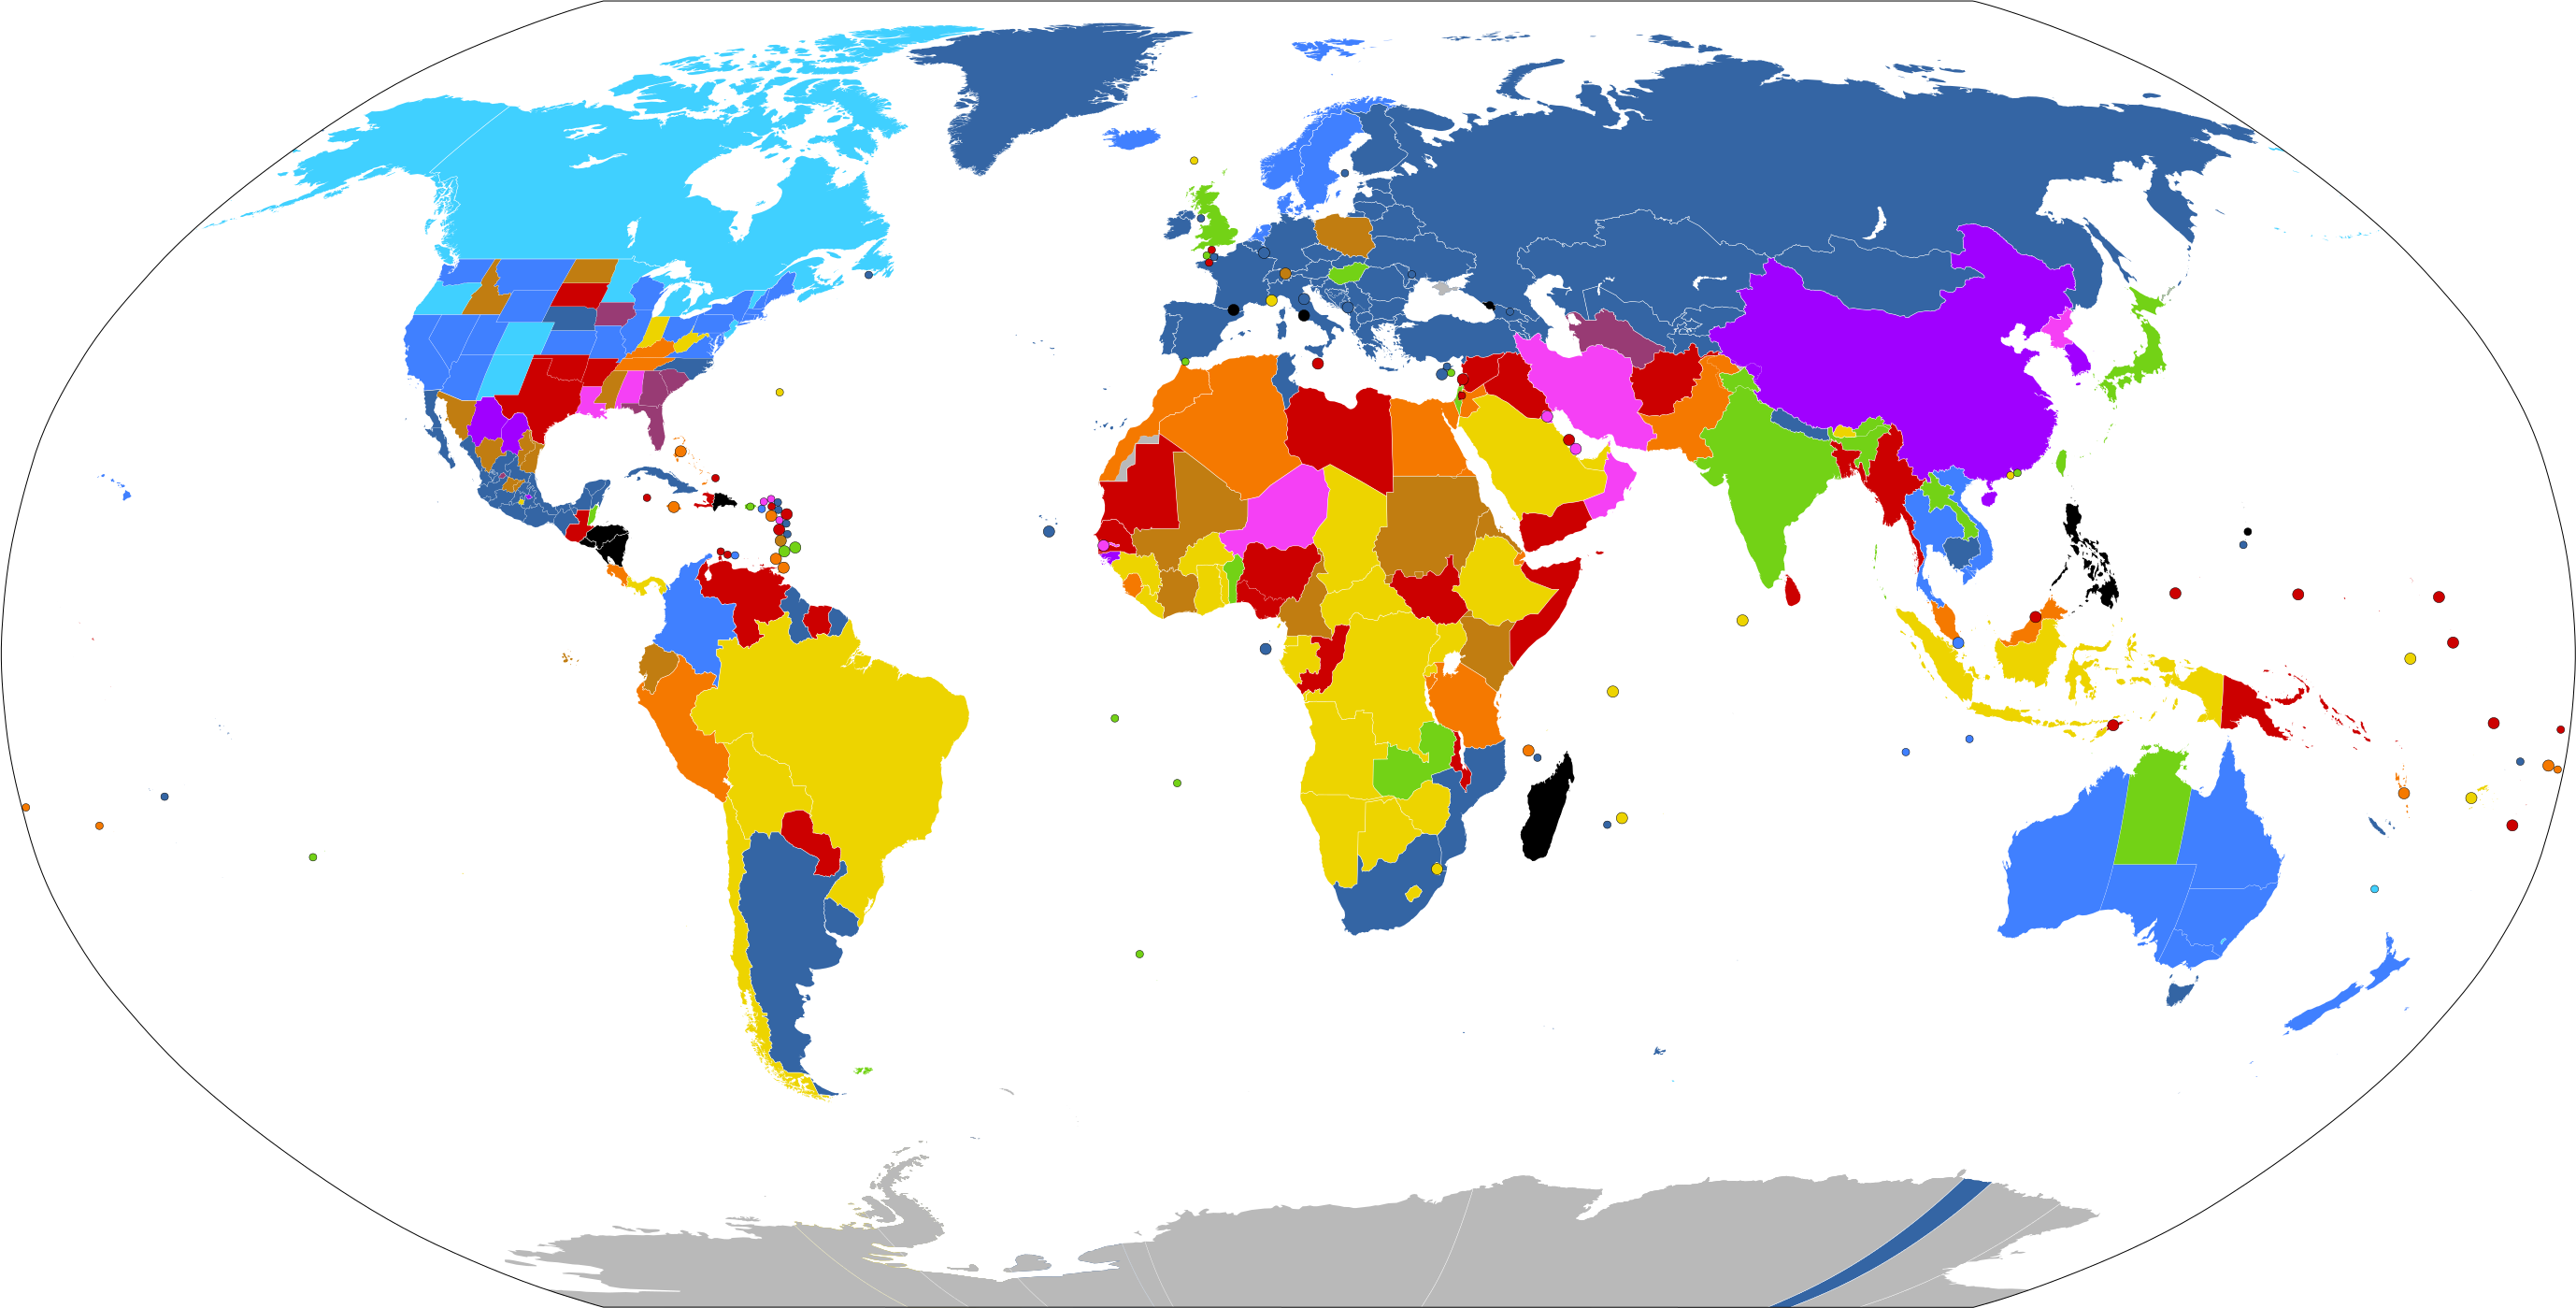
Wikimedia Commons, “Abortion Laws” — based on the Center for Reproductive Rights’ classification (Center for Reproductive Rights 2024).
Four Global Tiers
The Center for Reproductive Rights groups countries into four tiers by legal grounds.
| Tier | Grounds | Examples | % of reprod.-age women |
|---|---|---|---|
| I. Prohibited | None, or only implicit necessity | El Salvador, Nicaragua, Senegal, Egypt | ~5% |
| II. To save the woman’s life | Threat to life only | Nigeria, Iran, Indonesia, Brazil | ~22% |
| III. Health grounds | Plus mental/social/economic in some | UK, Finland, Israel, India, Japan | ~14% |
| IV. On request | No grounds, early in pregnancy | Canada, W. Europe, China, S. Africa, most of Latin America | ~36% |
Estimates from Center for Reproductive Rights, 2024 (Center for Reproductive Rights 2024; Roy and Klobucista 2024).
Activity — Why Does the World Converge Around 12–15 Weeks?
A striking pattern: nearly every liberal democracy that has settled the question — Germany, France, Italy, Belgium, Spain, the Netherlands, Argentina, Ireland — has landed on a first-trimester (or slightly later) on-request window, with stricter standards beyond it.
Write or discuss:
- What features of 12–15 weeks make it a natural settling point? Biological? Practical? Political?
- Why might the US have failed to reach such a settlement? (Hint: think about the difference between constitutional and legislative resolution.)
- Is convergence here evidence that this is the right answer, or only that it is a politically stable one?
Mini-Recap
Law has answered the abortion question in radically different ways across time and place: the common law treated early abortion as no crime; 19th-century America criminalized it everywhere; Roe and Casey read a privacy-and-liberty right into the Fourteenth Amendment; Dobbs returned the question to state legislatures; Latin America has liberalized while the US restricted. The argumentative tool from Part A travels: every Supreme Court opinion and every state statute can be put into standard form and tested at its load-bearing premise.
Review Questions
Recall
Pick two of the standard reasons a court gives for overturning one of its own past decisions. Which of the two did the most work in Dobbs?
Apply
A pharmacist in a ban state hesitates to fill methotrexate for a patient’s diagnosed ectopic pregnancy, worried the drug counts as an abortifacient. What should the clinician do, and what does the hesitation show about how bans reach care beyond abortion?
Debate
Should a ban’s medical exception list specific conditions, or leave the judgment to the treating physician? Defend one approach.
Key Terms
- Quickening — the first felt fetal movement; the common-law line below which abortion was not a crime.
- Precedent — a prior court decision treated as authoritative in later cases.
- Stare decisis — the presumption that courts should follow precedent unless very strong reasons compel otherwise.
- Trimester framework — Roe’s original standard, replaced in Casey.
- Undue burden — Casey’s standard: states may regulate but not place substantial obstacles before viability.
- Viability — the gestational point at which a fetus could plausibly survive outside the womb (~22–24 weeks).
- Trigger law — a state law written to take effect automatically when a Supreme Court precedent is overturned.
- Shield law — a state law protecting in-state providers from out-of-state legal action.
- Comstock Act — 1873 federal anti-obscenity statute that, on a literal reading, prohibits mailing abortion-related items.
References
Bioethics OER · CC BY-NC 4.0 · Brendan Shea