Lecture 9 — Public Health Ethics
Part A: From Patient to Population
1 A Healthy Woman in Quarantine
1.1 A Case to Sit With
It is 1907. Mary Mallon is a cook in New York City. She is healthy — she has never been sick a day in her life. But typhoid fever keeps breaking out in the families she cooks for: 22 cases so far, at least one of them fatal. Investigators believe her body carries the bacteria without harming her, and that she spreads it through the food she prepares.
She feels fine, has broken no law, and refuses to believe she is dangerous.
You are the health officer who must decide.
- May the city detain a healthy person who has committed no crime?
- If yes, for how long — and what would have to be true to justify it?
- What do you owe Mary in return for taking her freedom?
1.2 What the City Actually Did
Mary Mallon was the first known healthy carrier of typhoid in the US — and her story has two very different halves.
- First (1907–1910): officials seized her with no warning, no trial, and no precedent, and held her on North Brother Island for three years. No law yet said a well person could be locked up. She was released in 1910 after promising never to cook again.
- Second (1915–1938): she broke that promise. Under the alias “Mrs. Brown,” she took a kitchen job at Sloane Maternity Hospital and infected some 25 people, killing two — new mothers and staff. She was returned to the island until her death, about 26 years of confinement in all (Leavitt 1996).
These are not the same case — and by the end we will score them very differently.
1.3 After You’ve Discussed
Mary’s case is hard precisely because both sides have a real claim. She was harming people who never chose the risk. And she was a poor Irish immigrant woman, locked away for decades while other carriers were merely warned.
The clinical ethics you have learned so far asks: what does this patient want, and what is good for her? That framing cannot even state Mary’s problem — because the people who matter most here are the strangers she might infect.
Today we build the tools for that second kind of ethics — and we will come back to Mary at the end, where the two halves of her story pull in opposite directions.
1.4 Today
By the end of Part A, you will be able to:
- Explain how public health ethics differs from clinical ethics, and why the unit of concern shifts from the patient to the population.
- State Mill’s harm principle and explain why contagion is the case where it bites hardest.
- Apply Childress and colleagues’ five justificatory benchmarks to a real public health intervention.
- Trace a short history of public health — sanitation, vaccination, fluoridation, tobacco — and what made each one fought over.
- Reconstruct what Jacobson v. Massachusetts (1905) decided, and how the same logic was abused in Buck v. Bell.
2 From Patient to Population
2.1 Two Different Jobs
Clinical ethics and public health ethics answer to different patients.
| Clinical ethics | Public health ethics | |
|---|---|---|
| Unit of concern | the individual patient | the population |
| Primary value | autonomy — the patient’s own choice | collective welfare and fairness |
| Key relationship | doctor and patient, by consent | the state and a community, often without consent |
| Hard question | what does this person want? | who may be burdened for the good of all? |
This is not a different ethics. It is the same four principles — autonomy, beneficence, non-maleficence, justice — with the weight shifted from the individual to the population.
2.2 The Patient in Front of You Isn’t the Only Patient
In the clinic, the person who bears the risk and the person who makes the choice are usually the same. Public health pulls them apart.
- When Mary cooks, she runs no risk — the risk falls on the families at her table.
- When a parent declines a vaccine, the exposed include the newborn and the cancer patient who cannot be vaccinated at all.
- The decision and the danger sit with different people, which is exactly why consent alone cannot settle it.
What “population health” measures
Public health works in rates, not individuals. Incidence is how many new cases appear in a population over a period (say, measles cases per 100,000 per year). A measure that barely helps any single patient can still prevent thousands of cases once it is spread across a whole population.
3 Liberty vs. Collective Welfare
3.1 Mill’s Harm Principle
The starting presumption in a free society is liberty: adults may run their own lives, even badly. John Stuart Mill gave the classic limit.
“The only purpose for which power can be rightfully exercised over any member of a civilized community, against his will, is to prevent harm to others.” (Mill 1863)
Harm to yourself is not enough. The state needs harm to others to justify coercion — and that is the door public health walks through.
3.2 Why Contagion Is the Hardest Case
You met the harm principle when we asked whether the state may protect people from themselves. Infectious disease changes the problem, because the harm is no longer self-regarding.
- A drinker mostly endangers himself; a contagious person endangers strangers who never consented to the risk.
- One unvaccinated child raises the danger for everyone too young or too sick to be vaccinated — a cost imposed on others.
- So contagion is the cleanest case Mill allows: the choice genuinely reaches other people’s bodies.
Externalities and herd immunity
An externality is a cost your choice imposes on someone who had no say in it — like secondhand smoke. Vaccination creates the opposite, a benefit to others: once enough of a community is immune, the disease cannot spread easily, which protects the few who cannot be vaccinated. That shared shield is called herd immunity.
3.3 The Exception That Must Justify Itself
So public health is not a standing license to coerce. It is a standing exception to the presumption of liberty — and an exception has to earn its keep, every time.
That raises the question this whole lecture turns on:
When may a society override individual liberty for the sake of collective health — and how would we know when it has gone too far?
A slogan like “public safety” is not an answer. We need a test.
4 How Do We Know It’s Justified?
4.1 Five Benchmarks
James Childress — yes, the same Childress behind the four principles of biomedical ethics — and colleagues proposed five conditions a coercive public health measure should meet before we accept it (Childress et al. 2002). Think of them as a checklist that a mere appeal to “safety” must pass.
| Benchmark | The question it forces |
|---|---|
| Effectiveness | Will this actually work — is there real evidence it protects health? |
| Proportionality | Do the public benefits outweigh the burdens on liberty and privacy? |
| Necessity | Is coercion truly needed, or would a softer measure do? |
| Least infringement | Among options that work, is this the least restrictive? |
| Public justification | Can officials explain it openly to those who bear the burden? |
4.2 The Four Principles, Re-Tooled
That shared authorship is not a coincidence. These are not five new rules to memorize — they are the four principles you already know, retooled for populations.
| Benchmark | The principle it carries |
|---|---|
| Effectiveness + proportionality | beneficence weighed against non-maleficence |
| Necessity | non-maleficence — impose no more harm than required |
| Least infringement | respect for autonomy — minimize the liberty intrusion |
| Public justification | justice + accountability — answerable to those burdened |
The move from clinic to population doesn’t replace the principles. It re-weights them.
4.3 How to Use Them
The benchmarks do not give a yes-or-no verdict by themselves. They tell you what the argument is about — and where a policy is weakest.
- A measure can be effective yet fail proportionality (it works, but the cost to liberty is too high).
- It can be necessary yet fail least infringement (something had to be done, but not this).
- Most real disputes are not “liberty vs. safety” in the abstract; they are fights over one specific benchmark.
4.4 How to Read the Scoreboard
We score every major case against the same five benchmarks. The marks are not a tally — each reports the status of one dimension:
- ✅ clearly met — settled, not in dispute.
- ⚖️ the legitimate battleground — defensible either way; where honest people argue, not a weakness.
- ❌ fails — a genuine defect.
A measure can be fully justified while carrying several ⚖️s. Always read the bottom line, not the column of marks.
4.5 The Scoreboard: Mary’s First Detention (1907)
Applied first to her first detention — three years, on no precedent at all:
| Benchmark | Verdict | Why |
|---|---|---|
| Effectiveness | ✅ | She truly was an active carrier; isolation stopped the spread. |
| Proportionality | ⚖️ | Three years of liberty against a real but rare risk — arguable. |
| Necessity | ⚖️ | Was detention needed, or untried supervision? They never found out. |
| Least infringement | ❌ | No trial, no warning, indefinite — straight to the harshest option. |
| Public justification | ❌ | No law authorized it, and other carriers were spared her fate. |
This is the hard case for the state, and the genuinely troubling one: novel, no due process, indefinite, and she was singled out — a poor Irish immigrant woman. Effectiveness is solid; least infringement and justification are where it bites. Watch what happens to these marks at the second detention.
5 The Wins and the Resistance
5.1 Sanitation: The Broad Street Pump
In 1854, cholera was killing people in London’s Soho, and most experts blamed “bad air.” The physician John Snow mapped where the dead lived and saw the deaths cluster around one water pump on Broad Street (Snow 1855).
He persuaded officials to remove the pump handle. The outbreak, already fading, ended — and Snow had founded modern epidemiology: find the cause by studying the pattern in a population.
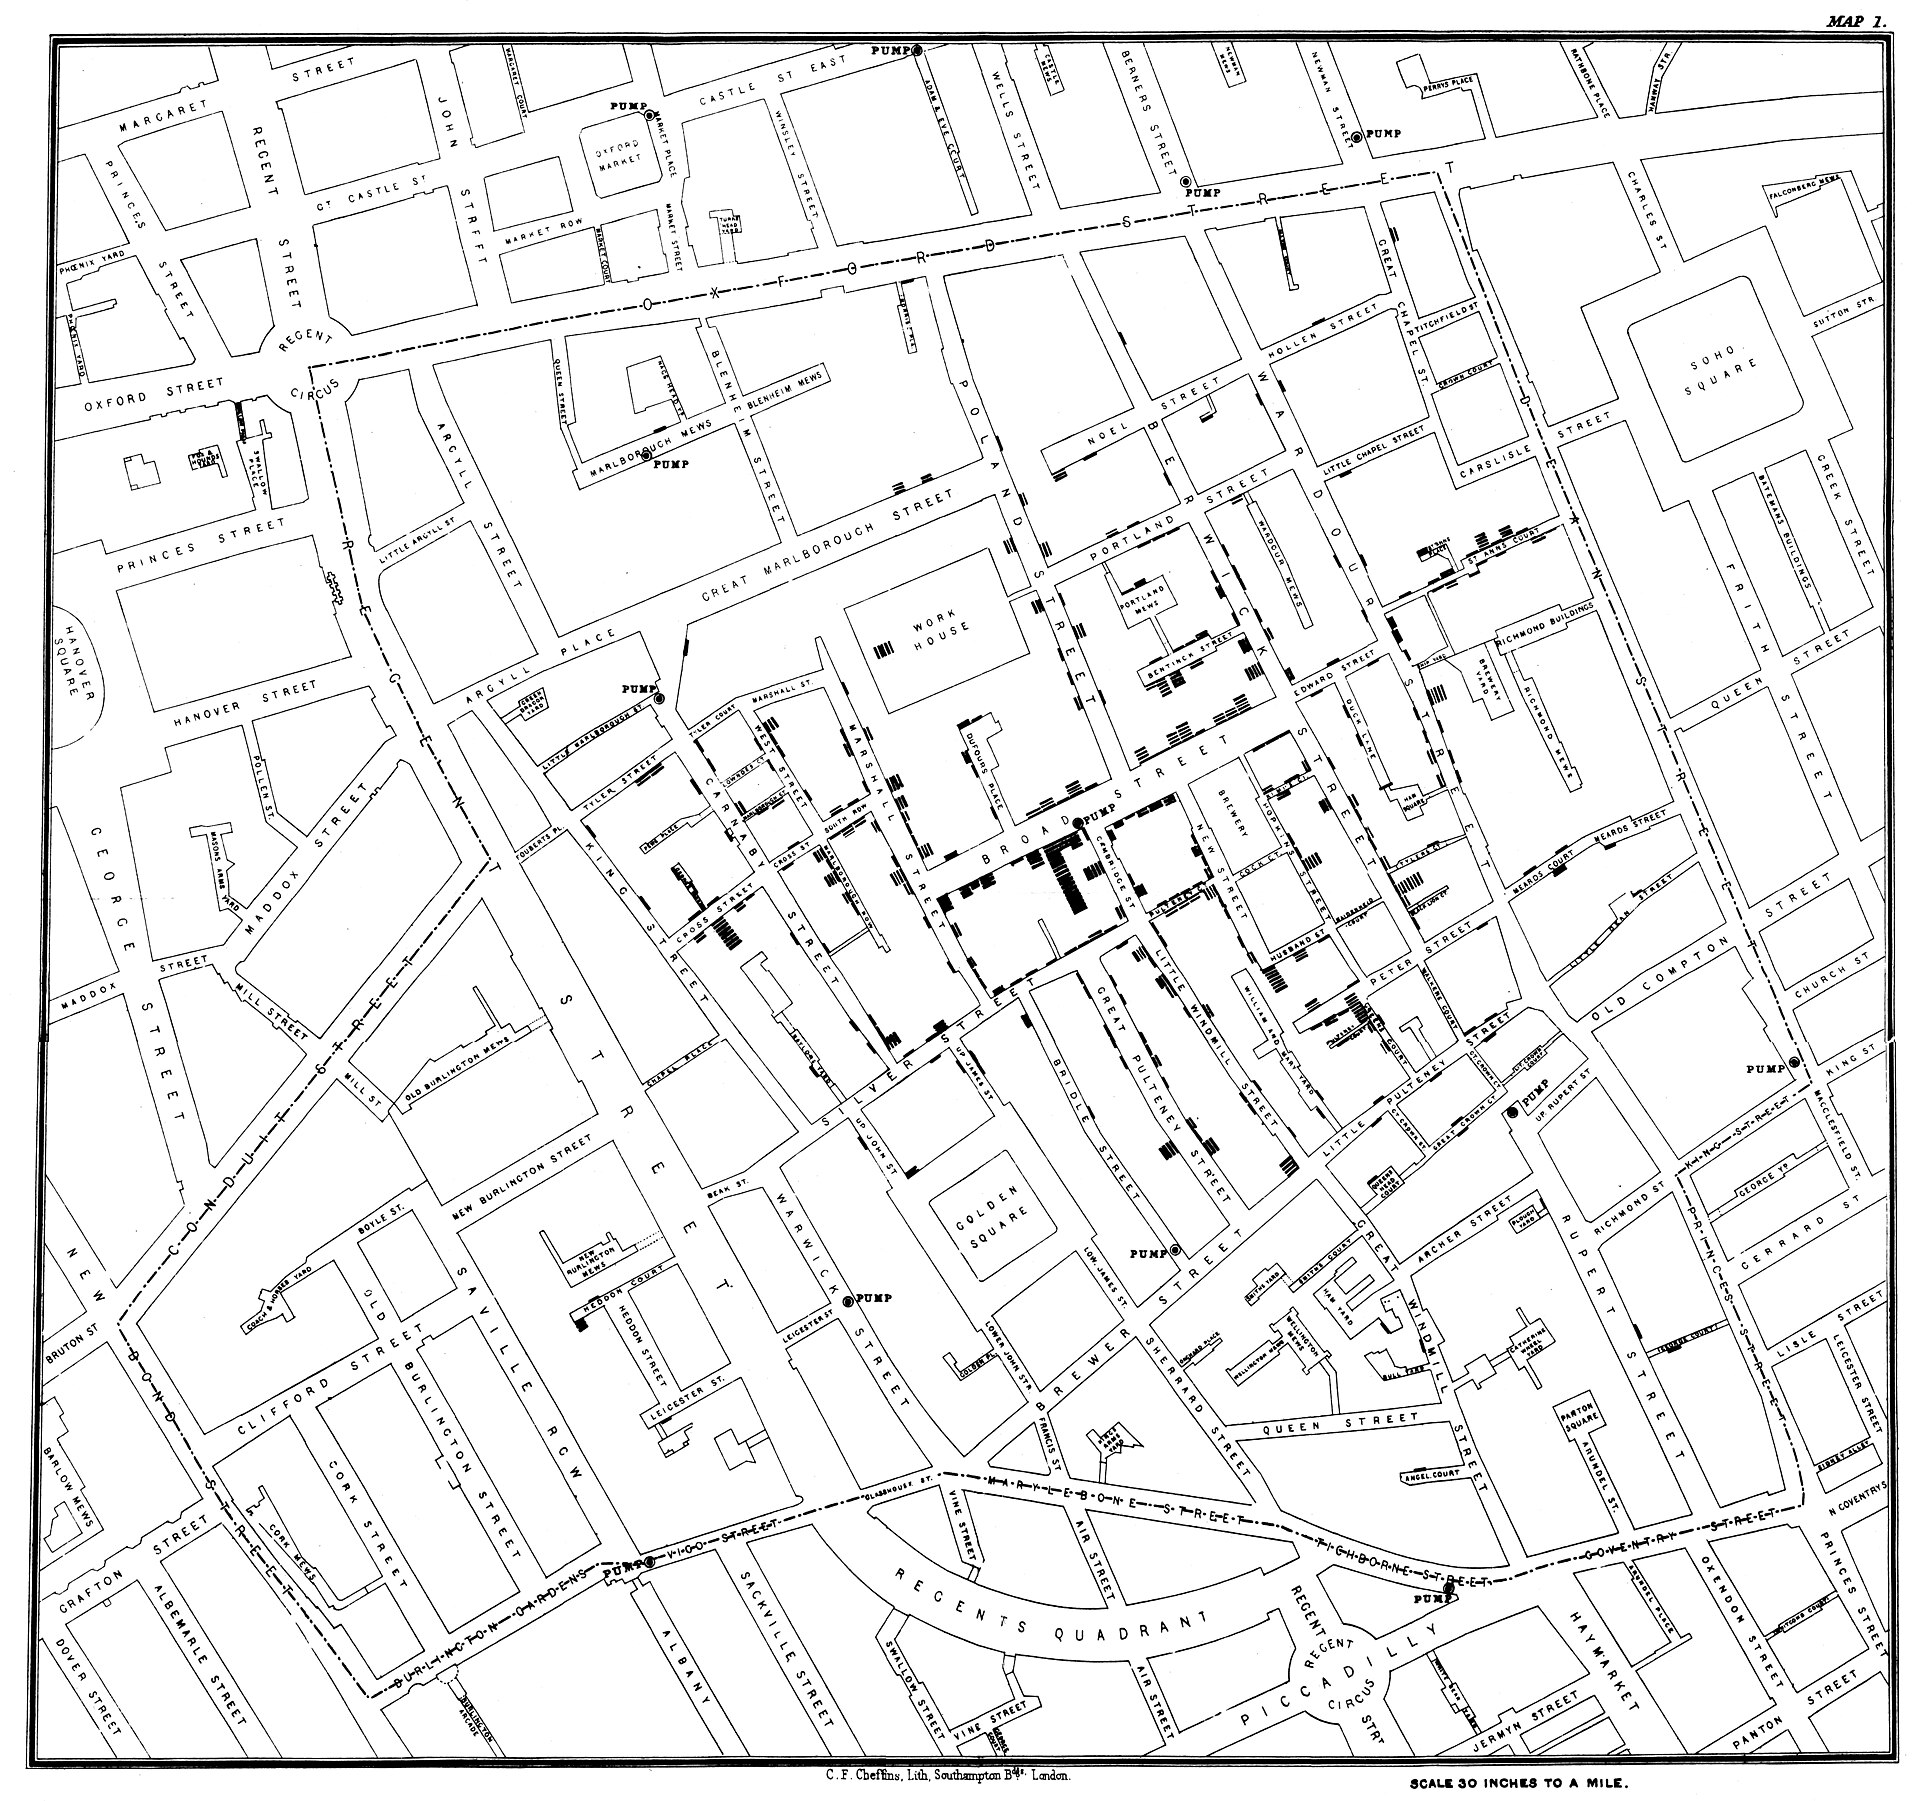
John Snow, cholera map of Soho, 1854. Public domain.
5.2 Sanitation — Scored
Clean water and sewers are among the largest life-savers in public health history — by some measures adding more years to life than any single drug.
| Benchmark | Verdict | Why |
|---|---|---|
| Effectiveness | ✅ | Waterborne epidemics collapsed once supplies were separated from sewage. |
| Proportionality | ✅ | Enormous benefit; the burden was mostly money and regulation, not liberty. |
| Necessity | ✅ | No individual can build their own clean-water system. |
| Least infringement | ✅ | It restricts pollution and plumbing, not persons. |
| Public justification | ✅ | The case is open, measurable, and widely shared. |
About as close to an easy case as public health gets: strong on every benchmark, with little serious dispute. Treat it as the contrast class — most of the cases that follow are not this clean.
5.3 Vaccination: From Scourge to Memory
Smallpox killed roughly 30% of those it infected and disfigured most survivors. After Edward Jenner’s 1796 cowpox vaccine, mass vaccination drove it back.
- In 1980 the World Health Organization declared smallpox eradicated — the only human disease ever deliberately wiped out.
- Measles cases in the US fell from hundreds of thousands a year to near zero after the 1963 vaccine.
- These are among the clearest public health wins on record — which makes the resistance they met worth taking seriously.
5.4 The Resistance Had Real Roots
Vaccination has drawn organized opposition since the very beginning, and the early fears were not all baseless.
- Early smallpox vaccination used arm-to-arm transfer that could pass along other infections; the safety worry had a real basis at the time.
- Victorian Anti-Vaccination Leagues framed compulsory vaccination as the state forcing a foreign substance into a child’s body — a liberty claim, not only a medical one.
- The lesson for the benchmarks: a measure can be highly effective and still owe people honest answers on proportionality and consent.
5.5 Vaccination — Scored
| Benchmark | Verdict | Why |
|---|---|---|
| Effectiveness | ✅ | Among the best-evidenced interventions in all of medicine. |
| Proportionality | ✅ | Serious harms are rare; the disease burden prevented is vast. |
| Necessity | ⚖️ | Live question: how high must uptake go, and is a mandate the only route? |
| Least infringement | ⚖️ | Real debate: narrow-exemption school rules may reach uptake with less force. |
| Public justification | ✅ | The evidence is open — though trust must be earned. |
The science is settled; the lasting argument is over coercion — how strong a mandate, which exemptions, in which circumstances. “Justified” here does not mean “case closed.”
5.6 Two Kinds of Criticism
Not every objection to a mandate is equal. The benchmarks let you sort the serious ones from the rest.
| Unreasonable objection | Why it fails | Legitimate objection | Why it’s serious |
|---|---|---|---|
| “Vaccines don’t work” | loses on effectiveness — the evidence is settled | “A less coercive design might reach similar uptake” | a real least-infringement question |
| “Just let it rip” | loses on proportionality — it discounts the deaths | “Make exemptions only as narrow as the threat needs” | turns on contested, checkable facts |
The pattern: unreasonable criticism attacks a ✅ benchmark that is actually settled. Legitimate criticism lives at the ⚖️ marks — is there a route that delivers the same benefit with less coercion? The honest answer is often “maybe — but it isn’t clear there is.”
5.7 Fluoridation: Medicine in the Water
Adding tiny amounts of fluoride to public water cuts tooth decay across a whole population, rich and poor alike — the CDC named it one of the great public health achievements of the 20th century.
- It is genuinely effective and cheap, and it reaches children whose families could never afford a dentist.
- But critics call it compulsory mass medication: unlike a vaccine you can refuse, the only way to opt out of the tap is to not drink the water.
- Here the fight is not about effectiveness at all. It is about consent and the right to refuse a benefit chosen for you.
5.8 Fluoridation — Scored
| Benchmark | Verdict | Why |
|---|---|---|
| Effectiveness | ✅ | Decades of data show real reductions in tooth decay. |
| Proportionality | ✅ | Benefit is large; the dose is far below any level of harm. |
| Necessity | ⚖️ | Live question: can toothpaste and dental programs match its reach for the poor? |
| Least infringement | ⚖️ | Real objection: there is no easy individual opt-out from the tap. |
| Public justification | ✅ | Openly debated and voted on in many localities. |
Evidence for benefit is strong, but this remains a live political fight — over consent and opt-out, and over optimal dose — that communities still vote on today.
5.9 Tobacco Control: A Ladder, Not a Ban
Smoking once filled offices, planes, and hospital wards. Public health rolled it back not with a single prohibition but with a ladder of escalating, ever-firmer steps.
- Inform: warning labels and the 1964 Surgeon General’s report.
- Tax: make the harmful choice more expensive without forbidding it.
- Protect others: smoke-free laws in workplaces and restaurants — aimed squarely at secondhand smoke, the externality.
Each rung climbs only as far as the harm to others justifies — a worked example of least infringement.
5.10 Tobacco — Scored
| Benchmark | Verdict | Why |
|---|---|---|
| Effectiveness | ✅ | US adult smoking fell from ~42% (1965) to 9.1% (2025) — below 10% for the first time. |
| Proportionality | ✅ | Smoke-free laws impose mild burdens against large health gains. |
| Necessity | ✅ | Voluntary appeals alone had stalled; secondhand smoke harms bystanders. |
| Least infringement | ✅ | It taxes and zones the behavior, not bans the product. |
| Public justification | ✅ | Grounded in openly published, overwhelming evidence. |
The core case is strong, yet the hard questions stay open: how high the tax, what age limit, whether to ban menthol or flavored vapes. The ladder is still being climbed.
5.11 1918: The Year of Masks and Closures
The influenza pandemic of 1918–19 killed an estimated 50 million people worldwide and about 675,000 in the US. There was no vaccine and no antibiotic — cities had only non-pharmaceutical interventions (NPIs): closing schools, churches, and theaters, banning gatherings, and requiring masks.
- Philadelphia held a wartime parade in late September 1918; within weeks its hospitals were overwhelmed and deaths soared.
- St. Louis closed early and stayed closed; its peak death rate was a fraction of Philadelphia’s.
- Timing and NPIs measurably saved lives — the first clear evidence that “flattening the curve” works.
5.12 1918 — Scored
San Francisco’s mask order drew an organized Anti-Mask League in early 1919, with thousands protesting compulsory masking as tyranny — and “closure fatigue” eroded compliance as the months wore on.
| Benchmark | Verdict | Why |
|---|---|---|
| Effectiveness | ⚖️ | Earlier, longer NPIs tracked lower peaks — but the size, and which measures mattered, is debated. |
| Proportionality | ⚖️ | Real benefit, but closures hit workers, shops, and churches hardest. |
| Necessity | ✅ | With no vaccine or cure, NPIs were the only tools available. |
| Least infringement | ⚖️ | Blanket closures are blunt; targeted measures barely existed in 1918. |
| Public justification | ❌ | Wartime secrecy and mixed messaging undercut trust. |
Non-pharmaceutical interventions clearly helped, but how much, and which ones, is genuinely debated — public health rarely gets a clean experiment. The clearest failures in 1918 were candor and execution, not the decision to act.
5.13 COVID-19: The Same Playbook, a Different World
A century later, COVID-19 reached for the same toolkit — distancing, masking, closures, then vaccines — but at a scale and duration 1918 never saw, in a connected, polarized society.
- The early NPIs again bought time, but fatigue, economic cost, and politicization frayed compliance far faster than in any single 1918 city.
- Public response split along identity and trust lines in ways that the 1918 Anti-Mask League only hinted at.
- Why people came to disbelieve the measures — the problem of false belief and broken trust — is the subject of Part B; here we are only tracking the measures and the response.
5.14 Two Pandemics, One Lesson
| 1918 influenza | COVID-19 | |
|---|---|---|
| Main tools | closures, gathering bans, masks | distancing, masks, closures, then vaccines |
| What seems to have helped | early, sustained NPIs tracked lower peaks (size debated) | early NPIs likely slowed spread (how much debated); vaccines clearly cut deaths |
| Why compliance frayed | closure fatigue, business cost, war secrecy | fatigue, economic cost, politicization, distrust |
The deep lesson repeats: NPIs can help, but their power is limited less by biology than by how long a public will accept them — which is why trust, not just law, decides a pandemic. And because public health rarely runs a clean experiment, how much any one measure helped is itself often argued for years.
5.15 Thought Question
Many places require motorcycle helmets and seatbelts. A rider who skips a helmet seems, at first, to risk only himself — which Mill’s harm principle would protect.
- Is helmet-skipping really self-regarding, or does it impose costs on others? Name them.
- Does “society pays the medical bills” justify almost any health mandate? Where would that logic stop?
- Which of the five benchmarks does a helmet law pass most easily — and which is shakiest?
5.16 After You’ve Discussed
Both arguments turn on the same point. The helmet debate is really about whether a “self-regarding” choice stays self-regarding once its costs are socialized — shared through insurance, emergency rooms, and lost income.
That gives us a useful distinction the benchmarks alone don’t name: a direct externality (your germs enter my body) versus a socialized cost (we all pay for the consequences of your risk). The first is the strong Millian case for coercion; the second is real but far easier to stretch into justifying anything. Keep them apart.
5.17 What the History Shows
Across four very different interventions, the benchmark that decides the case keeps changing.
| Case | The benchmark that does the work |
|---|---|
| Sanitation | passes all five — the easy case |
| Vaccination | fought over least infringement (mandate vs. exemption) |
| Fluoridation | fought over least infringement / consent (no opt-out) |
| Tobacco | a model of least infringement done well (the ladder) |
The real disputes are rarely “freedom vs. safety.” They are arguments about which benchmark a specific policy flunks.
6 Jacobson and Its Shadow
6.1 Jacobson v. Massachusetts (1905)
During a smallpox outbreak, Cambridge required adults to be vaccinated or pay a $5 fine (about $170 today). Pastor Henning Jacobson refused and challenged the law.
- The Supreme Court upheld the requirement, grounding it in the state’s police power to protect public health.
- The Court’s key idea: individual liberty is not absolute, and a community may protect itself against an epidemic that threatens everyone.
- This remains the legal foundation for US vaccine requirements more than a century later (Supreme Court of the United States 1905).
6.2 What Jacobson Actually Decided
Read the holding narrowly. Jacobson is often described as letting the government force needles into arms. It did no such thing.
- The penalty was a fine, not forced vaccination. Jacobson could refuse and pay.
- The Court demanded the measure be reasonable and tied to a real public necessity — not arbitrary.
- It even warned that such powers could go “beyond what was reasonably required” and harm particular people — a limit, written into the very case that grants the power.
6.3 The Court’s Own Words
“There are manifold restraints to which every person is necessarily subject for the common good. On any other basis organized society could not exist with safety to its members.”
“Real liberty for all could not exist under the operation of a principle which recognizes the right of each individual person to use his own [liberty]… regardless of the injury that may be done to others.”
— Jacobson v. Massachusetts, 197 U.S. 11 (1905) (Supreme Court of the United States 1905)
6.4 Buck v. Bell: The Same Logic Abused
Twenty-two years later, the Court cited Jacobson to reach one of its most criticized results.
- In Buck v. Bell (1927), it upheld the forced sterilization of Carrie Buck, a young woman wrongly labeled “feeble-minded,” as a public health measure for the “welfare of society.”
- Justice Holmes wrote: “Three generations of imbeciles are enough.” The science was unfounded and the label was false (Supreme Court of the United States 1927).
- The same “necessity for the common good” that justified a $5 vaccine fine was stretched to justify the forced sterilization of people judged unfit — part of the American eugenics story you met earlier.
6.5 Why the Benchmarks Exist
Run Buck v. Bell through the scoreboard. It is not a close call — it fails almost everything.
| Benchmark | Verdict | Why |
|---|---|---|
| Effectiveness | ❌ | Based on pseudoscience; sterilizing Carrie Buck protected no one. |
| Proportionality | ❌ | An irreversible bodily harm against a non-existent threat. |
| Necessity | ❌ | No public danger required any action at all. |
| Least infringement | ❌ | Irreversible surgery forced on a healthy body. |
| Public justification | ❌ | Built on a false label the subject could not contest. |
The benchmarks are not bureaucracy. They are the guardrails that separate Jacobson from Buck.
Flatly unjustified — the one case on this scoreboard that fails every benchmark. Unlike Mary Mallon, who at least passed effectiveness, Buck involved no real threat at all.
7 When May the State Compel?
7.1 Thought Question
You are a nurse on an oncology unit, where patients have weakened immune systems. Your hospital adopts a policy: get an annual flu shot, or wear a mask at all times on duty during flu season. A respected colleague refuses both, calling it a violation of her bodily autonomy.
- Is this a “mandate”? She is never held down — she has an alternative (the mask).
- Which patients’ interests are on the other side of her refusal?
- Run the policy through the five benchmarks. Does it pass?
7.2 Make It Contemporary
In 2019, a large measles outbreak spread through under-vaccinated communities in New York. In response, New York repealed its religious exemption to school vaccine requirements, leaving only medical exemptions. Unvaccinated children could no longer attend school.
- Is barring a child from school a fine-like penalty (à la Jacobson), or something heavier?
- Does ending a long-standing exemption during an outbreak strengthen or weaken its public justification?
- Would you have kept a narrow exemption? On which benchmark does your answer turn?
7.3 After You’ve Discussed
“Mandate” hides at least three different tools, and they sit at different rungs of the least-infringement ladder:
- A pure mandate removes the choice (forced vaccination — which, note, Jacobson did not authorize).
- A condition of participation keeps the choice but attaches a cost: vaccinate or don’t attend school, or wear a mask.
- A taxed or incentivized choice leaves the act fully free but tilts it (a surcharge, a paid day off to get the shot).
Almost every real “vaccine mandate” is the second kind. Naming which tool is in play is usually more clarifying than arguing about “mandates” in general.
8 Back to Mary
8.1 The Second Detention Flips the Scoreboard
The first detention was the hard case. The second is not — and the same benchmarks now point the other way.
| Benchmark | 1907 (first) | 1915 (second) |
|---|---|---|
| Effectiveness | ✅ | ✅ |
| Proportionality | ⚖️ | ✅ — she had killed again, by deceit |
| Necessity | ⚖️ | ✅ — the softer rung was tried, and failed |
| Least infringement | ❌ | ⚖️ — release-on-promise had already failed once |
| Public justification | ❌ | ✅ — a documented, willful return to the kitchen |
By 1915 she had used a false name and cooked at a maternity hospital, infecting the most vulnerable patients there. The least-infringing option had been offered — and she broke it.
8.2 So What Did Mary Teach Us?
The lesson is not “the government got it wrong.” It is sharper and more useful than that.
- The same coercion can be unjustified in 1907 and justified in 1915 — because the facts changed, not the slogan.
- In 1907 the state skipped the softer rungs; in 1915 it had climbed them and watched them fail.
- “Detain the carrier” is never the right answer or the wrong one in the abstract. The benchmarks — and the four principles inside them — decide, case by case.
8.3 Make It Contemporary
Mary’s dilemma is not history. We still confine — and even prosecute — contagious people who will not change their behavior.
- TB isolation: US courts can still order a contagious, non-adherent tuberculosis patient into involuntary isolation — the direct legal descendant of Mary’s island.
- HIV nondisclosure laws: since the late 1980s, many states criminalize exposing a partner to HIV without disclosure. Reformers say the laws ignore real transmission risk and deter testing; defenders point to deliberate, deceptive exposure — the “Mrs. Brown” case.
- Which detention does each law resemble — the 1907 case, or the 1915 one?
- Does criminal punishment meet “least infringement,” or fail the way the first detention did?
8.4 Mini-Recap
We moved from the clinic, where ethics turns on one patient’s choice, to the population, where the danger and the decision fall on different people. Mill’s harm principle opens the door to coercion when a choice truly harms others, and contagion is its sharpest case. But that license is an exception that must justify itself, so we adopted Childress’s five benchmarks — the four principles re-tooled for populations — and scored sanitation, vaccination, fluoridation, and tobacco against them. Mary showed that the same detention can pass or fail as the facts change; Jacobson shows the power at its most legitimate; Buck v. Bell shows the same logic abused, which is exactly why the benchmarks matter.
All of this was about what a society may compel. Next we turn to the harder modern problem: what public health can do when force is unavailable or unwise — when the obstacle is not defiance, but what people believe.
8.5 Review Questions
Recall
List Childress and colleagues’ five benchmarks and explain the difference between necessity and least infringement.
Apply
A city wants to ban sugary-drink sales over 16 ounces to fight diabetes. Pick two benchmarks and use them to argue for or against the ban.
Debate
Should states allow religious or philosophical exemptions to school vaccine requirements? Defend your view using the harm principle and at least one benchmark.
8.6 Key Terms
- Public health ethics — ethics whose unit of concern is the population, not the individual patient.
- Harm principle — power may be used against someone’s will only to prevent harm to others (Mill).
- Externality — a cost (or benefit) a choice imposes on people who had no say in it.
- Herd immunity — protection of the non-immune once enough of a population is immune.
- Police power — a state’s authority to regulate for public health, safety, and welfare.
- The five benchmarks — effectiveness, proportionality, necessity, least infringement, public justification (Childress et al.).
- Healthy carrier — a person who spreads a pathogen without being sick themselves.
- Condition of participation — a rule that keeps a choice but attaches a cost (e.g., vaccinate or stay home).
8.7 Further Reading
- Gostin, Lawrence O., and Lindsay F. Wiley. Public Health Law: Power, Duty, Restraint. University of California Press, 2016.
- Leavitt, Judith Walzer. Typhoid Mary: Captive to the Public’s Health. Beacon Press, 1996.
- Bayer, Ronald, et al., eds. Public Health Ethics: Theory, Policy, and Practice. Oxford University Press, 2007.